How Pituitary Growth-Hormone Secretagogues Work
In human physiology, the anterior pituitary gland secretes growth hormone (somatotropin) in discrete pulses—most notably during slow-wave sleep and following intense physical exertion. Growth hormone release is governed by a dual-control system in the hypothalamus:
- Growth Hormone-Releasing Hormone (GHRH): The accelerator pedal that binds GHRH receptors on somatotroph cells to stimulate GH synthesis and secretion.
- Somatostatin (GHIH): The brake pedal that inhibits GH release and prevents continuous baseline elevation.
- Ghrelin / Growth Hormone Secretagogue Receptor (GHS-R1a): A separate G-protein-coupled receptor that amplifies GH pulse amplitude and antagonizes somatostatin inhibition.
According to research published in the Journal of Clinical Endocrinology & Metabolism, secretagogue peptides preserve hypothalamic-pituitary negative feedback loops, whereas direct administration of synthetic recombinant human growth hormone (rhGH) suppresses endogenous pituitary production.
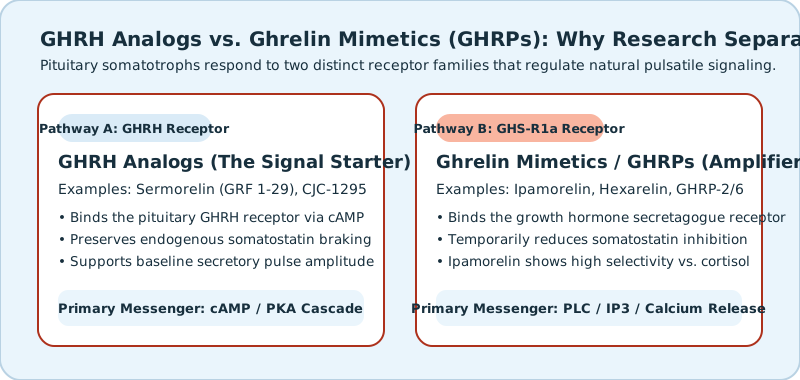
Comparing the Core Secretagogue Peptides
Although often grouped together in casual discussions, the four major secretagogues studied for body composition differ markedly in amino acid length, receptor selectivity, half-life, and regulatory classification.
| Compound | Receptor Target | Pharmacokinetic Half-Life | Hormonal Selectivity | U.S. Regulatory Status (Apr 2026) |
|---|---|---|---|---|
| Ipamorelin | GHS-R1a (ghrelin mimetic) | Short (hours) | High selectivity; minimal ACTH, cortisol, or prolactin rise | Unapproved; Ipamorelin acetate in Category 2 |
| CJC-1295 | Pituitary GHRH receptor | Short (without DAC) / Extended over several days (with DAC) | Preserves pulsatility while elevating mean GH/IGF-1 | Unapproved; nominated for Category 2 but withdrawn |
| Sermorelin | Pituitary GHRH receptor | Short (minutes) | Native GHRH(1–29) sequence; rapid enzymatic clearance | Previously FDA-approved (Geref); 503A compounding path |
| Hexarelin | GHS-R1a (ghrelin mimetic) | Short (hours) | Potent GH release, but elevates serum cortisol & prolactin | Unapproved investigational secretagogue |
1. Ipamorelin: Selective Pentapeptide Ghrelin Mimetic
Ipamorelin is a selective growth hormone secretagogue that mimics ghrelin at the pituitary GHS-R1a receptor. Earlier GHRPs such as GHRP-2 and GHRP-6 stimulated strong GH release but also triggered off-target increases in adrenocorticotropic hormone (ACTH), cortisol, and prolactin.
Research in the European Journal of Endocrinology discusses Ipamorelin’s ability to stimulate growth hormone release without desensitization.
2. CJC-1295: Synthetic GHRH Analog
CJC-1295 is a synthetic analog of Growth Hormone-Releasing Hormone (GHRH) engineered to resist rapid enzymatic cleavage in the bloodstream. In research catalogs, two distinct versions are discussed under this name:
- CJC-1295 without DAC (Mod GRF 1-29): A shorter-acting modified GHRH analog designed to produce brief, pulsatile GHRH receptor stimulation.
- CJC-1295 with DAC (Drug Affinity Complex): Incorporates an albumin-binding modification that extends its circulation time over several days.
Research from The Journal of Clinical Endocrinology & Metabolism demonstrates that CJC-1295 can increase growth hormone and IGF-1 levels for an extended period after administration while preserving pulsatile secretion.

3. Sermorelin: Native GHRH(1–29) Amide
Sermorelin is the 29-amino-acid N-terminal fragment of human GHRH—the shortest sequence that retains full biological activity at the pituitary GHRH receptor. Sermorelin acetate was previously FDA-approved under the brand name Geref for the diagnosis and treatment of pediatric growth hormone deficiency before being discontinued by its manufacturer for commercial (non-safety) reasons.
Because Sermorelin has a short half-life and relies on intact somatostatin feedback, it stimulates pulsatile pituitary GH release rather than continuous baseline elevation. Clinical studies and reviews in Clinical Interventions in Aging have reported improvements in lean body mass, body composition, and exercise capacity in adults with growth hormone deficiency or age-related GH decline, while noting that outcomes in clinical deficiency populations do not automatically translate to healthy athletic populations.
4. Hexarelin: High-Potency Hexapeptide GHRP
Hexarelin is a synthetic hexapeptide ghrelin mimetic that produces strong acute GH release in endocrine studies. However, compared with Ipamorelin, clinical studies show that Hexarelin causes more pronounced elevations in serum cortisol and prolactin and exhibits faster receptor desensitization during repeated administration.
How Secretagogues Compare to Nutrition, rhGH, and Anabolic Steroids
Understanding where pituitary secretagogues sit in exercise physiology prevents unrealistic expectations:
- Resistance Training & Dietary Protein: Mechanical tension, progressive overload, and sufficient leucine/amino acid intake activate the intracellular mTORC1 pathway directly inside myofibers. Secretagogues do not replace mechanical stimulus.
- Exogenous Human Growth Hormone (rhGH): Direct rhGH administration bypasses pituitary feedback, frequently causing fluid retention, carpal tunnel compression, arthralgia, and insulin resistance.
- Anabolic-Androgenic Steroids (AAS): Bind nuclear androgen receptors to drive rapid myofibrillar protein synthesis, but suppress the hypothalamic-pituitary-gonadal axis and carry severe cardiovascular and hepatic toxicity.
On FDA's Bulk Drug Substances page current as of April 22, 2026, CJC-1295 and PEG-MGF are listed as nominated for 503A Category 2 but withdrawn, while GHRP-2, GHRP-6, and Ipamorelin acetate remain listed on the FDA's Category 2 Bulk Drug Substances list due to safety risks. Sermorelin has a distinct regulatory history as a discontinued FDA-approved product not withdrawn for safety reasons. Human safety during pregnancy or breastfeeding is unestablished for investigational peptides and growth hormone secretagogues. Furthermore, all GHRH analogs and ghrelin mimetics are strictly banned at all times under Section S2 of the World Anti-Doping Agency (WADA) Prohibited List.